
Diverse functions of an anti-aging hormone, Klotho
Sep 15th 2026
The discovery of the klotho gene was published in Nature in 1997. The authors identified the disrupted gene and named it “klotho,” after the Greek goddess, Clotho, who spins the thread of life. Mice with defective klotho gene expression exhibited a syndrome that resembles human aging whereby mice aged rapidly and died young.1
Immuno-Biological Laboratories Co., Ltd., Japan, organized a conference where “Diverse Functions of an Anti-Aging Hormone, Klotho” was a topic. A summary of this informative presentation follows.
What does Alpha-klotho (a-klotho) do?
A-klotho is a membranous protein expressed in renal tubular cells. A-klotho forms a dimer structure with the Fibroblast Growth Factor (FGF) receptor to act as a receptor for the protein FGF23. When FGF23 binds to the FGF receptor/klotho dimer, phosphorus reabsorption is inhibited by the kidney decreasing blood phosphorus levels. A-klotho also suppresses 1,25-dihydroxyvitamin D synthesis, thereby reducing intestinal absorption of calcium resulting in lower blood calcium concentrations. Thus, in renal tubular cells, a-klotho functions as a co-receptor for FGF23 regulating phosphorus and calcium metabolism.
Mice deficient in a-klotho exhibit a variety of aging phenotypes, including atherosclerosis, osteoporosis, skin atrophy, and ectopic calcification. The lifespan of these deficient mice is ~60 days; whereas wildtype normal mice survive for ~ 100 days. Transgenic mice carrying and expressing the klotho gene have a 20-30% increased lifespan for both males and females.1,2
Mice with reduced klotho gene expression exhibit hyperphosphatemia. When these mice are fed a low-phosphorus diet, the aging phenotype improved with blood phosphorus level reduction, suggesting that hyperphosphatemia may accelerate the aging process. Many of the aging phenotypes in a-klotho-deficient mice can be explained by “hyperphosphatemia”.3
How may Klotho be measured?
The soluble form of a-klotho is produced by proteolytic cleavage of the extracellular domain of the full-length transmembrane protein. ADAM10 or ADAM17 may cleave at the root of the extracellular domain and also at specific sites to generate KL1 and KL2 fragments. Thus, releasing membranous a-klotho and soluble a-Klotho forms into circulation.4
A sandwich ELISA was developed to quantify soluble a-klotho concentrations utilizing 50 uL samples with results generated in under three hours. This assay was used to quantify the relationship between age and blood klotho levels revealing soluble a-klotho levels decrease with increasing age.5 A decline in renal function was also associated with decreased soluble a-klotho levels.6
What are functions of Soluble a-Klotho?
Soluble a-klotho circulating in the blood has a multitude of anti-aging functions: acts as an antioxidant, has anti-inflammatory action, protects against chronic fibrosis and cardiovascular-related diseases, tumor suppression, metabolic modulation related to diabetes mellitus, cellular senescence inhibition, stem cell preservation and neurodegenerative diseases protection. A-klotho is synthesized by the kidneys and circulates in the blood to suppress aging-related diseases by exerting diverse physiological effects on various tissues and organs. Consequently, klotho acts as anti-aging hormone.4
Let’s examine these anti-ageing functions in more detail:
Reduction of oxidative stress by a-klotho
Oxidative stress is a condition where excess reactive oxygen species are found in the body. Reactive oxygen species are highly reactive oxygen-related molecules containing extra electrons that may be responsible for accelerated aging. For example, when lipid peroxides are deposited in blood vessels, arteriosclerosis occurs leading to cardiovascular diseases, such as myocardial infarction and stroke. There are mechanisms in the body to counteract these reactive oxygen species. One of these is the detoxification of reactive oxygen species by antioxidant enzymes such as manganese-containing superoxide dismutase (SOD) and hemeoxygenase-1 (HO-1).
There are two main pathways for the expression of these antioxidant enzymes. One pathway involves Forkhead box class O (FoxO). Normally, signals transmitted by insulin-like growth factors (IGF) keep FoxO in the cytoplasm, but a-klotho inhibits IGF from binding the IGF receptor, resulting in the translocation of FoxO into the nucleus and promoting the expression of the antioxidant enzyme genes.7
Klotho also acts on the nuclear factor erythroid 2-related factor 2 (Nrf2) pathway. This is thought to promote nuclear translocation of Nrf2, which in turn promotes antioxidant enzyme gene expression. A-klotho promotes Nrf2-mediated expression of antioxidant enzyme genes in vascular endothelial cells. When recombinant a-klotho is added to cultured vascular endothelial cells, Nrf2 degradation is inhibited while intracellular Nrf2 is increased. Furthermore, Nrf2 promotes the expression of antioxidant enzyme genes such as HO-1 and Prx-1.8
Anti-inflammatory action of a-klotho
Inflammation is a biological defense response whereby macrophages and other cells release cytokines in response to microbial infection, physical or chemical stimuli. These cytokines activate various immune cells. Chronic inflammation results in the destruction of normal tissues causing age-related diseases. Similarly, chronic obstructive pulmonary disease (COPD), characterized by damaged bronchi and alveoli, results in breathing problems. Most COPD is caused by smoking. The anti-inflammatory effect of a-klotho was studied using an in vitro COPD mouse model. Stimulation of mouse alveolar macrophages with tobacco smoke extract increased the production of inflammatory cytokines such as TNF-a and IL-6. However, prior addition of a-klotho inhibited release of inflammatory cytokines following the stimulation with tobacco extract. Gene expression of inflammatory cytokines is mainly regulated by a transcription factor called nuclear factor kappa light chain enhancer of activated B cells (NFkB). NFkB binds to an inhibitor found in the cytoplasm, where interaction of klotho appears to limit nuclear translocation of NFkB.9
Suppression of fibrosis by a-klotho
Fibrosis is a condition where repair of damaged tissue is uncontrolled resulting in excessive production of extracellular matrix (ECM). Normal tissue is destroyed by this unrestricted ECM production leading to pulmonary fibrosis in the lungs, cirrhosis of the liver and glomerulonephritis in the kidneys. The mechanisms of these fibroses are similar. Fibroblasts in the lung, astrocytes in the liver, and mesangial cells in the kidney transform into myofibroblasts upon stimulation by TGFβ or other factors. Myofibroblasts continue to proliferate actively, producing ECM such as collagen and fibronectin and destroying normal tissue. TGFβ signals are transmitted to the nucleus through the smad pathway and the Ras, Raf, and ERK pathways, activating transcription of fibrosis-related genes, including a-smooth muscle actin, a myofibroblast marker, and ECM proteins such as collagen and fibronectin. Klotho is thought to inhibit the binding of TGFβ to the TGF-receptor, therefore suppressing TGFβ signaling to the nucleus and inhibiting the fibrosis. By blocking TGFβ signaling, a-klotho suppresses fibroblast differentiation into myofibroblasts, thereby inhibiting fibrosis.10
The inhibitory effect of klotho on fibrosis was studied using a model of cultured mouse lung fibroblasts. Adding TGFβ to the fibroblast cultures enhanced the expression of a-smooth muscle actin, collagen, and fibronectin. However, when recombinant a-klotho was added to the cultures prior to the addition of TGFβ, the expression of these fibrosis-related genes was not enhanced by the addition of TGFβ.11
Tumor suppressive action of a-klotho
The growth suppressive effect of a-klotho was studied using human pancreatic tumor cells (Panc1) cultured with a-klotho for 48 hours. Viability of Control cells without a-klotho was defined as 100%, addition of a-klotho suppressed cell proliferation 30-70%. Both the addition of human a-klotho or mouse a-klotho to Panc1cells suppressed cell proliferation. Human a-klotho was more effective at lower concentrations than adding mouse a-klotho. When pancreatic cancer cells were transplanted into nude mice and treated with 10 mg/kg or 25 mg/kg daily a-klotho, tumor size was reduced as compared to non-klotho treated control mice. A-klotho seems to exert its growth suppressive effect by inhibiting IGF signaling and bFGF signaling.12
Has Klotho been measured in U.S. National Health and Nutrition Examination Survey (NHANES) samples?
Yes. This NHANES program is conducted by the Centers for Disease Control and Prevention (CDC) to assess health and nutritional status of the US population. Serum klotho levels were measured in over 13,000 human samples collected between 2007- 2016 using IBL's ELISA kit. Results were disclosed approximately five years later. More than 130 papers on cohort studies from these collected samples have been published. These papers described the association of serum a-klotho levels with various diseases, mortality, diet, toxic substances/environmental pollution, sleep, and smoking and other factors as shown in the following table:
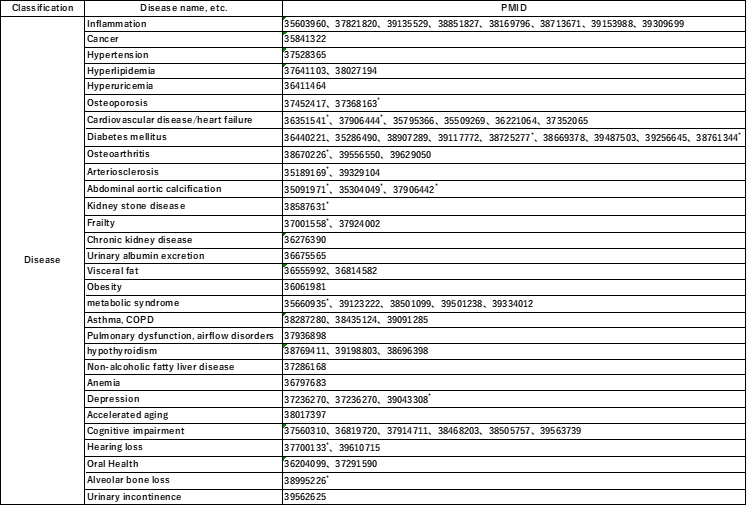
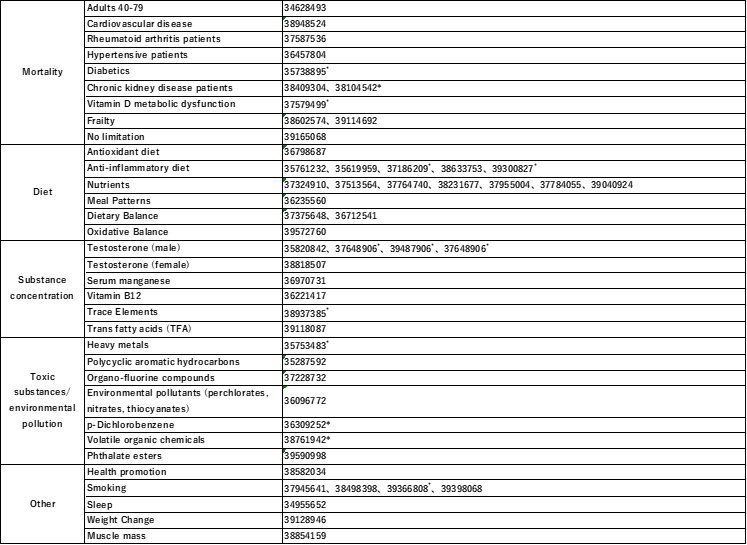
To examine some of these relationships in more detail:
Blood a-klotho level and inflammation
As described previously, inflammation is a biological defense response. There are two types of inflammation: acute inflammation or chronic inflammation. Acute inflammation is what often comes to mind with symptoms including fever and swelling. On the other hand, chronic inflammation is a mild inflammation that persists for a long period of time, often without symptoms. According to a recent theory, this chronic inflammation is thought to promote aging. The term “Inflammaging” has even been coined by adding the words ‘inflammation” and "aging”. The relationship between four inflammation markers: uric acid (UA), C-reactive protein (CRP), white blood cell count (WBC) and mean platelet volume (MPV) with serum a-klotho levels was examined in samples from more than 11000 NHANES participants. For each inflammation marker, results were divided into 4 quartiles, Q1-Q4, with Q1 having the lowest values. UA was most strongly associated with a-klotho levels with higher UA values coinciding with decreasing a-klotho levels. A similar pattern was seen with CRP and WBC; whereas lower MPV levels resulted in increased a-klotho values as MPV levels decrease with increased inflammation. All four biomarkers exhibited strong associations with a-Klotho in the higher quartiles. A-klotho may serve as an indicator of inflammation level.13
Blood a-klotho level and risk of cardiovascular disease
The associations between α-Klotho and four specific cardiovascular diseases were examined in over 8500 NHANES samples. Congestive heart failure (CHF) and myocardial infarction (MI) had a linear inverse correlation with serum a-klotho levels where the risk of disease increased as a-klotho levels decreased. A trend for a rise in disease risk for coronary heart disease and stroke was seen with lower a-klotho levels. More research is needed to further elucidate the relationship between a-klotho and cardiovascular diseases.14
Blood a-klotho level and risk of osteoarthritis
Osteoarthritis (OA) is commonly seen in older individuals as the cartilage cushion erodes in joints. This degenerative joint disease leads to pain, stiffness and decreased mobility. In 8918 NHANES samples, a linear inverse relationship between serum a-klotho levels and the risk of osteoarthritis was seen. Individuals with lower serum a-klotho levels are at a higher risk of developing osteoarthritis.15
Association between blood a-klotho level and frailty
Frailty refers to physical and mental weakness due to aging, and the relationship between a-klotho and frailty has also been investigated using NHANES samples. Frailty is assessed by the Frailty Index, which is calculated from 53 items related to depressive symptoms, comorbidities, hospital, physical ability/measurements, and laboratory measurements. There is an inverse linear correlation between the relationship for serum a-klotho levels and frailty risk using data from over 9000 NHANES individuals.16 The relationship between serum a-klotho levels and the risk of low muscle mass was also studied using 3800 NHANES samples. An inverse correlation was observed between a-klotho levels and risk of muscle mass loss.17 Finding ways to elevate a-klotho levels may help maintain muscle mass and prevent frailty allowing a healthier old age.
Association between blood a-klotho level and phenotypic age
Some people are younger or older than their chronological age. In contrast to the chronological age that increases year by year, phenotypic age is based on the actual condition or function of the body. Phenotypic age is calculated using chronological age and nine aging-related biomarkers. The first study looking at phenotypic aging with NHANES was published in 2018. The authors noted that younger phenotypic age group lived longer in all generations of chronological age, demonstrating the validity of the phenotypic age concept.18
Samples from 2007-2010 NHANES participants (n=4388, age 40-79 years) with a-klotho measured were separated into quintiles, based on serum a-klotho concentrations. A U-shaped relationship existed between serum a-klotho and the aging speed of phenotypic age. In other words, the aging speed of phenotypic age increased when the serum a-klotho levels were either too high or too low. The majority of participants had a-klotho levels below 1,000 pg/mL, so within this range, an inverse relationship was observed: the lower the a-klotho concentration, the faster the phenotypic aging rate.19
Association between blood a-klotho level and mortality
The relationship between α-Klotho and mortality was examined using 2007-2016 NHANES samples (n=13749, age 40-79 years). Values were separated into five quintile groups with survival curves plotted for death from all causes, cancer, cardiovascular disease and other causes for each quintile. The group with lower blood a-klotho levels exhibited higher all-cause mortality, cancer mortality, cardiovascular mortality, and other-cause mortality.20
Based on NHANES data, there appears to be relationships between blood a-klotho levels with diseases, aging rates, and mortality. These statistical analyses can prove a relationship between blood a-klotho concentration and the risk of developing a disease, but they cannot show a causal relationship between the two, namely, which came “first” and which is “the result”. This begs the question does blood a-klotho levels decrease when diseases develop?
To try to answer this question, the expression of the klotho gene was examined using a rat model. Deoxycorticosterone acetate (DOCA) salt hypertensive rats had lower a-klotho mRNA expression levels than control rats. In addition to hypertension, cholesterol and blood glucose levels were higher in the DOCA rats. It is not clear what is affecting the klotho expression, but there is no doubt that klotho expression is decreased in rats with these pathological conditions.
Similarly, klotho expression in type 2 diabetic rats compared to normal rats was measured. Diabetic rats had higher blood glucose, heavier body weight, higher cholesterol and triglyceride levels than controls. Decreased expression of the klotho gene has been observed in rats with hypertension or type 2 diabetes pathology.21
As previously described, klotho-deficiency results in accelerated aging-like phenotypes. To determine if proinflammatory cytokines, such as TNF and TNF-like weak inducer of apoptosis (TWEAK), modulate klotho, exogenous TNF-a or TWEAK were added to cultured mouse tubular cells. Klotho mRNA expression decreased. This down regulation of klotho is through an NFκB-dependent mechanism. Aging-related diseases such as cardiovascular disease, cancer, diabetes, osteoarthritis, and Alzheimer's disease are well known to be accompanied by chronic inflammation and the release of inflammatory cytokines, resulting in a-klotho gene expression.22
Klotho declines with age. Decreased klotho raises the risk of aging-related diseases and, indeed, may lead to kidney disease, diabetes, cardiovascular-related diseases, and so on. And with disease, klotho declines further, further increasing the risk of disease. In this negative spiral, the blood klotho level will decline below a certain threshold, which accelerates the aging process and shortens the lifespan. What can be done to prevent this negative spiral? Is it possible that the anti-aging effects attributed to some modifiable lifestyle factors are due to increased a-klotho concentrations?
Can exercise increase a-klotho levels? Twelve 20-year-old untrained men performed five sets of ten repeated leg extensions. A single bout of resistance exercise increase klotho levels, when klotho was measured ten minutes after exercise completion. However, thirty minutes after the physical activity ended, klotho levels returned to pre-exercise levels.23
What happens with training? Two groups of women (25-45 and 65-74 years old) walked one hour on the treadmill. Blood was collected before and after acute exercise. Subjects then completed 16 weeks of training by cycling, rowing, walking, etc. At the end of the training period, the women again performed the acute exercise of one hour walking on the treadmill. Klotho levels increased from the original reading to after the 16-week training period. It was statistically different for the young women with a blunted response seen in the older cohort. Since the sampling was done after acute exercise, it is unknown if the baseline klotho levels are elevated.24
Another study looked at athletes and non-athletes to see if klotho levels differed. Football players (n = 30; 18-22 years old) were compared with healthy non-athletes (n=28; 18-27 years old), klotho levels were significantly higher without significant differences in cholesterol, triglycerides, calcium, or phosphorus levels. The increase in baseline circulating klotho may help explain the beneficial effects of exercise on healthy aging.25
Can diet influence a-klotho levels? Chronic inflammation is a factor that plays a role in ageing. Some foods are considered to be anti-inflammatory while others are pro-inflammatory. The Dietary Inflammation Index (DII) classifies individual diets from the most anti-inflammatory to the most pro-inflammatory by measuring the effect of food on six inflammation markers: IL-1β, IL-4, IL-6, IL-10, TNF-α, and CRP. Negative numbers are given to foods that have a high anti-inflammatory effect. Examples of low DII foods are vegetables such as garlic, ginger, onions, vitamins, dietary fiber, and so-called omega-3 fatty acids such as DHA and EPA. An anti-inflammatory or low DII diet increases a-klotho levels.26 Similarly, higher dietary fiber intake was associated with higher a-klotho levels in blood.27
Adherence to a Mediterranean diet has been reported to reduce morbidity and mortality. The Mediterranean diet is characterized by consumption of fish, vegetables, olive oil, and red wine. To quantify adherence, scores were assigned from 0 (minimal adherence) to 18 (maximal adherence) for the different portions consumed per day to calculate a total Mediterranean Diet Adherence Score.28 Blood a-klotho levels increase as the Mediterranean Diet Adherence Score increases. It is not an individual factor but rather a healthy, balanced diet that is responsible for the increase in serum a-klotho levels.29
Obesity may also be deleterious to health. What happens if a person loses weight? Does a-klotho increase? Individuals participating in NHANES (n= 590) experienced a significant weight reduction from obese to non-obese during the middle to late adulthood. The time period was ten years. Interestingly, in these individuals, the larger the weight reduction, the higher the klotho levels. A decrease in body weight of 1 kg is calculated to increase the klotho concentration by approximately 3 pg/mL.30
Can drugs influence klotho levels? Besides increasing klotho levels by lifestyle modifications of diet and exercise, drugs may also raise klotho levels. Losartan is an angiotensin II receptor blocker (ARB) and is one of the most prescribed antihypertensive drugs. When type 2 diabetics were given Losartan, klotho levels increased after four weeks of starting therapy. ARBs other than Losartan may have similar effects. Other drugs such as fluvastatin, pentoxifylline, vitamin D, sirolimus, and everolimus are known to increase blood klotho levels. In addition, diabetic drugs such as GLP-1RA, DPP-4 inhibitors, metformin, and PPAR-γ agonists have also been shown to increase klotho levels in animal studies. Thus, klotho levels may increase using different strategies.31
Does a-klotho help in the removal of senescent cells by senolytics? Senescent cells are cells that have arrested cell division due to cellular senescence and secrete senescence-associated secretory phenotype (SASP) factors such as inflammatory cytokines, chemokines, and extracellular matrix degrading enzymes, causing chronic inflammation and other problems in surrounding cells. The accumulation of senescent cells may accelerate aging. When young mice are inoculated with senescent cells artificially produced by irradiation, the amount of a-klotho in their urine decreases. Since this effect was believed to be caused by SASP factors, Activin A for renal epithelial cells and IL-1α for astrocytes have the effect of reducing klotho. Clearing the senescent cells restores a-klotho.
There are known drugs that can reduce senescent cells when administered orally, and these drugs, or the administration of drugs to remove senescent cells, are called senolytics. Senolytics have been shown to improve physical function and increase survival rates in aging mice. Administration of dasatinib, a synthetic anticancer drug, and quercetin, a naturally sourced drug found in onions and other plants, reduced senescent cells and increased klotho in the urine. A similar effect has also been shown with fisetin, a naturally sourced substance found in strawberries and other plants. Dasatinib and quercetin have also been administered in human clinical trials, where urinary klotho increased after administration. Incidentally, quercetin and fisetin can be purchased as dietary supplements. Senolytics eliminate senescent cells and increase a-klotho.32
Does administration of a-klotho improve cognitive function? Klotho is thought to play important functions in the brain, including protection against neurodegenerative diseases. Rhesus monkeys, average age 21.8 years equivalent to humans 65 years old, were administered 10 µg/kg of recombinant klotho. Their cognitive function was measured at 4 hours and 14 to 23 days later. Cognitive function was tested by a spatial delayed response task. Surprisingly, a single administration of low dose recombinant klotho at 10 µg/kg improves cognitive function at 4 hours and at the later time points. In addition to recombinant klotho, gene and cell therapies targeting klotho appear to be under development, mainly by U.S. startup companies. Other attempts are underway to raise a-klotho through gene therapy and cell therapy.33
In conclusion, in addition to the mineral metabolic function as a co-receptor for FGF23, klotho has a variety of functions as an anti-aging hormone, including antioxidant, anti-inflammation, fibrosis inhibition, and tumor suppressive effects. Decreased blood klotho levels increase the risk of various aging-related diseases and frailty. Klotho is useful as a biomarker for various diseases and frailty. Exercise and dietary modifications increase blood klotho levels, which may reduce the risk of aging-related diseases. Drugs and supplements may also raise blood klotho levels. Gene therapies are also being developed. Ultimately, elevating klotho levels may slow aging and lengthen the healthy lifespan with the goal of living a healthy life as long as possible.
Humankind has long searched for a fountain of youth. More functions of klotho are yet to be discovered and what the future holds for klotho research. IBL-America offers assay kits for both mouse and human a-klotho. Please visit the IBL-America website (IBL America Online Store) for more information on these and our other offerings.
Citations
1Kuro-o M et al. Nature. 1997. PMID: 9363890
2Kurosu H et al. Science. 2005. PMID: 16123266
3Kuro-o M. J Atheroscler Thromb. 2021. PMID: 33028781
4Prud'homme GJ et al. Front Aging. 2022. PMID: 35903083
5Yamazaki Y et al. Biochem Biophys Res Commun. 2010. PMID: 20599764
6Rotondi S et al. Int J Endocrinol. 2015. PMID: 25873958
7Donate-Correa J et al. Antioxidants (Basel). 2023. PMID: 36829798
8Maltese G et al. J Cell Mol Med. 2017. PMID: 27696667
9Li L et al. J Biol Chem. 2015. PMID: 26385922
10Kim SH et al. Int J Mol Sci. 2022. PMID: 35563402
11Huang Q et al. Aging (Albany NY). 2020. PMID: 32244228
12Abramovitz L et al. Clin Cancer Res. 2011. PMID: 21571866
13Wu SE et al. Ann Med. 2022. PMID: 35603960
14Xu JP et al. Front Cardiovasc Med. 2022. PMID: 35795366
15Qiu Y et al. PLoS One. 2024. PMID: 39556550
16Yuan M et al. Am J Transl Res. 2024. PMID: 39114692
17Xie Y et al. Front Nutr. 2024. PMID: 38854159
18Liu Z et al. PLoS Med. 2018. PMID: 30596641
19Li H et al. BMC Geriatr. 2023. PMID: 38017397
20Sadr N et al. Br J Clin Pharmacol. 2024. PMID: 39165068
21Nagai R et al. Cell Mol Life Sci. 2000. PMID: 10892340
22Moreno JA et al. J Am Soc Nephrol. 2011. PMID: 21719790
23Morishima T and Ochi E. Physiol Rep. 2021. PMID: 34713986
24Avin KG et al. Front Physiol. 2014. PMID: 24987372
25Mostafidi E et al. Nephrourol Mon. 2016. PMID: 26981496
26Ma TC et al. Front Nutr. 2022. PMID: 35619959
27Liu S et al. Nutrients. 2023. PMID: 37513564
28Sofi F et al. Public Health Nutr. 2014. PMID: 24476641
29Wu SE et al. Nutrients. 2022. PMID: 36235560
30Chen S et al. Sci Rep. 2024. PMID: 39128946
31Lim SC et al. Renin Angiotensin Aldosterone Syst. 2014. PMID: 23380567
32Zhu Y et al. EBioMedicine. 2022. PMID: 35292270
33Castner SA et al. Nat Aging. 2023. PMID: 37400721